
Few sounds define pregnancy like the swift, steady beat of your baby’s heart, first heard as a fast whoosh-whoosh at an early ultrasound. Beyond the emotional reassurance, that heartbeat is a vital sign — a window into your baby’s development and wellbeing. This guide walks through the whole journey: when the heart begins to beat, what counts as normal at each stage, how your care team monitors it, and the real limits of trying to listen at home.
The First Heartbeat and Normal Ranges
Your baby’s cardiovascular system is the first to function. Around week 5, a primitive heart tube forms and begins a rhythmic motion. By weeks 6–7, a first flicker of cardiac activity may be visible on a transvaginal ultrasound, often around 110 beats per minute (BPM). By week 9, the four chambers are largely formed and the rate climbs quickly. You may first see this at your first prenatal appointment.
What counts as normal shifts as pregnancy progresses:
- First trimester (weeks 6–13): starts around 110 BPM at 6 weeks and peaks around weeks 9–10, often reaching 140–170 BPM (sometimes higher). There’s a wide normal range during this rapid development.
- Second and third trimesters (week 14 to delivery): the rate settles into an established normal range of 110 to 160 BPM, fluctuating within it as a sign of a healthy, responsive nervous system.
A key point: a single number matters less than the pattern and variability. A healthy heartbeat isn’t metronomic — it rises and falls with your baby’s sleep cycles, movements, and even outside sounds, and that variability is exactly what your provider listens for.
How Your Care Team Monitors the Heartbeat
- The fetal Doppler at prenatal visits: from around 10–12 weeks, your midwife or OB uses a handheld Doppler that translates the motion of the heart valves into sound. Finding it can take a moment depending on the baby’s position, your anatomy, and where the placenta sits.
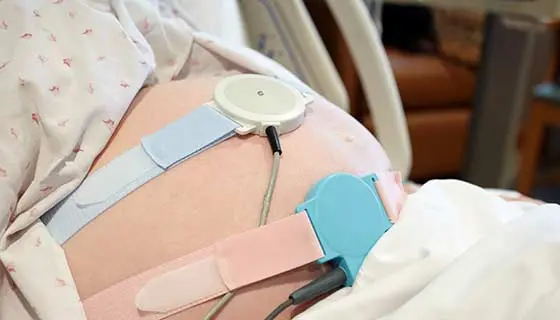
- The non-stress test (NST): in the third trimester — especially for a high-risk pregnancy, reduced movement, or going past your due date — two belly sensors track the heart rate and contractions while you mark movements. A “reactive” result (two or more heart-rate accelerations with movement in 20 minutes) is very reassuring.
- The biophysical profile (BPP): combines an NST with an ultrasound scoring five factors — breathing movements, body movements, muscle tone, amniotic fluid, and the NST. Our guide to the biophysical profile explains it in detail.
- Electronic fetal monitoring in labor: your baby’s heart rate is tracked to see how it responds to contractions, usually with external belly sensors, or occasionally a tiny scalp electrode for a more precise continuous reading. The team watches for reassuring patterns and responds to non-reassuring ones (repositioning, fluids, or, if needed, expediting delivery).
The Home Doppler Dilemma
The urge to hear that heartbeat at home is completely understandable, and consumer Dopplers are sold widely online — but they come with real cautions:
- Misidentification: before 12–14 weeks it’s very easy to pick up your own aortic pulse or placental blood flow and mistake it for the baby.
- False reassurance: hearing a heartbeat doesn’t confirm wellbeing — it says nothing about growth, fluid, or oxygenation, and a problem can exist alongside a “normal”-sounding rate.
- Unnecessary anxiety: not finding the heartbeat is common even for professionals (it depends on position), and can cause panic when all is well.
- Delayed care: most seriously, relying on a home Doppler can delay you calling your provider about decreased movement or other concerns.
If you do use one, treat it strictly as a bonding experience, not a medical tool: wait until at least 12–14 weeks (16–18 is more realistic), set a 5–10 minute limit and stop if you don’t find it, and never use it to “check on” the baby instead of calling your provider about a concerning symptom.
The Best Home Practice: Counting Movements
From around 28 weeks, paying attention to your baby’s movements is a far more meaningful daily indicator of wellbeing than any heart-rate check, because movement correlates directly with a healthy nervous system. To do a kick count, pick a time your baby is usually active (often after a meal), lie on your side or sit comfortably, and count how long it takes to feel 10 distinct movements (kicks, rolls, jabs). Most babies reach 10 within 20–30 minutes, and you should feel them within 2 hours. What matters most is your baby’s normal pattern and any change from it.
If you notice a significant decrease in movement, do not reach for a Doppler — call your provider right away. That’s the single most empowered thing you can do, and it’s one of the key third trimester warning signs.
Patterns You Might Hear About
Interpretation is for professionals, but it helps to recognize the terms:
- Tachycardia: a sustained rate above 160 BPM, which can follow maternal fever, infection, activity, or medications.
- Bradycardia: a sustained rate below 110 BPM, which needs prompt evaluation, especially in labor.
- Decreased variability: a rate that’s too steady — often just a deep sleep cycle, but if persistent it can signal distress.
- Decelerations: temporary dips. Some are normal with contractions in labor (early decelerations); others (late or variable) can be non-reassuring and prompt intervention.
Frequently Asked Questions
Not necessarily. In the first trimester, rates can be quite high (peaking around 9–10 weeks) and then gradually slow. A rate of 180 at 12 weeks may be at the upper end but is often a normal variant, especially if your baby was active. Your provider looks at the overall context.
No. This is an old wives’ tale with no scientific basis. Fetal heart rate varies with gestational age, activity, and your baby’s own physiology — not biological sex.
Still 110–160 BPM. In labor the focus shifts to how the rate responds to contractions — your team watches for accelerations and monitors for any concerning decelerations, adjusting your care as needed.
Yes, very commonly. Your abdominal aorta runs down your midline and pulses at your own slower resting rate (around 60–100 BPM), feeling like a deep, steady thud. The fetal heartbeat is much faster (roughly 120–160 BPM) with a galloping, whooshing quality.
Variability reflects a healthy nervous system. Staying hydrated, managing stress, and keeping blood sugar steady (especially with gestational diabetes) all support a healthy environment. If a test raises concerns, discuss them directly with your provider.
The Bottom Line
Tracking your baby’s heart rate is a partnership between you, your baby, and your care team. The technology — from the first flicker on an ultrasound to the monitor in labor — serves one purpose: a safe journey. Your most powerful tool isn’t a device you can buy, but your own attuned awareness, and paying attention to your baby’s movement patterns is the single best daily practice. Attend your prenatal checks, use a home Doppler (if at all) with clear eyes about its limits, and call your provider with any concern — you are the most connected monitor your baby has.
This article is for general information and is not a substitute for personalized medical advice. Contact your provider with any concern about your baby’s movements or heartbeat.
References
- American College of Obstetricians and Gynecologists (ACOG). Special Tests for Monitoring Fetal Well-Being.
- American College of Obstetricians and Gynecologists (ACOG). Fetal Heart Rate Monitoring During Labor.
- Mayo Clinic. Nonstress test.
